Gonadorelin Acetate
Extensively StudiedDecapeptide
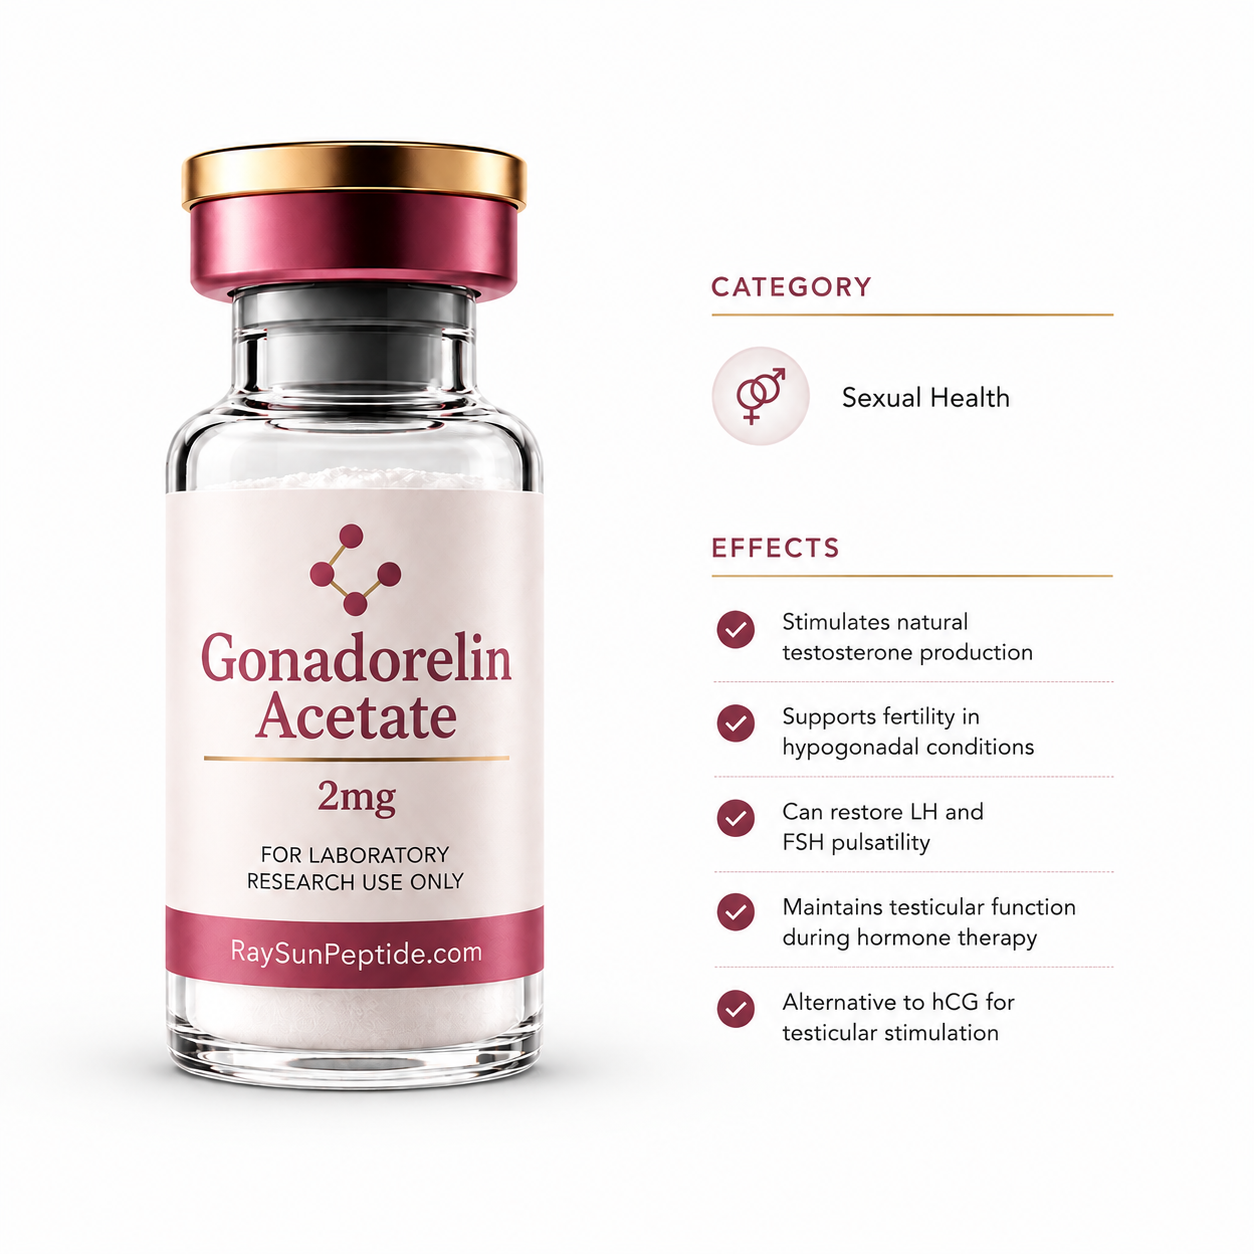
Gonadorelin is a synthetic decapeptide identical to gonadotropin-releasing hormone (GnRH). It has been extensively studied in reproductive endocrinology research for its role in stimulating gonadotropin release from the anterior pituitary. Published research has investigated its effects on the hypothalamic-pituitary-gonadal axis in various laboratory models. RaysunPeptide supplies Gonadorelin Acetate for qualified research and laboratory applications.
Mechanism of Action
Gonadorelin acts as an agonist of the GnRH receptor in the anterior pituitary. When administered in pulses (mimicking natural secretion patterns every 60-120 minutes), it stimulates release of FSH and LH. LH then stimulates Leydig cells in the testes to produce testosterone, or triggers ovulation in women. Continuous exposure paradoxically causes receptor downregulation and suppressed hormone production.
Key Benefits
Molecular Data
Dosing Protocols
| Goal | Dose | Frequency | Route |
|---|---|---|---|
| Diagnostic testing | 100 mcg | Single injection | SubQ or IV |
| Fertility support | 50-100 mcg | 2-3x weekly | SubQ |
| Pulsatile therapy | 5-20 mcg per pulse | Every 90-120 min | SubQ pump |
| TRT adjunct | 100-200 mcg | 2-3x weekly | SubQ |
Research Indications
Fertility & Reproductive
Treatment of conditions like Kallmann syndrome where GnRH deficiency causes low testosterone and infertility.
Induces ovulation in women with hypothalamic amenorrhea who don't ovulate regularly.
Stimulates testosterone and sperm production by restoring LH/FSH pulsatility.
Treatment of delayed puberty due to hypothalamic-pituitary dysfunction.
Diagnostic
Used to assess hypothalamic-pituitary function and diagnose GnRH deficiency.
Evaluates pituitary reserve and responsiveness to GnRH stimulation.
Hormone Optimization
Maintains testicular function and fertility during testosterone replacement therapy.
Helps restore natural testosterone production after anabolic steroid use.
Treatment of undescended testes in pediatric patients.
Peptide Interactions
Often used as alternative to hCG for testicular stimulation during TRT.
Used alongside TRT to maintain testicular function and fertility.
Can be combined in fertility and PCT protocols.
Kisspeptin stimulates GnRH release; can work together for hormone optimization.
What to Expect
Side Effects & Safety
Common (Generally Mild)
- •Injection site reactions
- •Headache
- •Flushing
- •Nausea
- •Abdominal discomfort
Stop Signs (Seek Medical Attention)
- ⚠Signs of allergic reaction (rash, difficulty breathing)
- ⚠Severe headaches
- ⚠Unusual abdominal pain
Contraindications
- ✕Hormone-sensitive tumors
- ✕Pregnancy
- ✕Hypersensitivity to GnRH or analogs
- ✕Conditions worsened by sex hormone release
Quality Checklist
Good Signs ✓
- White lyophilized powder
- Clear solution after reconstitution
- Intact vacuum seal
Warning Signs !
- Slight clumping that dissolves easily
Bad Signs ✕
- Discolored powder
- Cloudy or particulate solution
- Broken seal
References
Pulsatile GnRH administration effectively restores fertility in patients with hypothalamic hypogonadism.
Pulsatile GnRH secretion (every 60-120 min) is essential for proper FSH/LH release and reproductive function.
Effective treatment for ovulation induction in women with hypothalamic amenorrhea.
FAQs
Why is pulsatile Gonadorelin dosing critical, and what happens with continuous dosing?
Gonadorelin must be dosed in pulses (every 90-120 minutes) to mimic natural GnRH secretion patterns. Continuous exposure paradoxically causes GnRH receptor desensitization and downregulation, suppressing LH and FSH release—the opposite of desired effects. Proper pulsatile timing is essential for therapeutic success.
Is Gonadorelin better than hCG for maintaining testicular function during TRT?
Both Gonadorelin and hCG maintain testicular function and fertility during TRT, but they work differently. hCG directly mimics LH with a 24-36 hour half-life, while Gonadorelin stimulates natural LH/FSH release but requires pulsatile dosing. hCG is simpler to administer; Gonadorelin offers more physiological restoration of the HPG axis.
How quickly does Gonadorelin raise testosterone after injection?
Gonadorelin has an extremely short 2-4 minute half-life, triggering LH release within minutes. Testosterone elevation from LH stimulation begins within hours, with peak levels at 6-12 hours post-injection. This rapid response makes it suitable for diagnostic testing and pulsatile protocols.
Can Gonadorelin be used long-term for post-cycle therapy, or just short-term?
Gonadorelin is effective for both acute (diagnostic) use and extended post-cycle protocols lasting 2-3 weeks. However, its extreme sensitivity to dosing frequency makes it less practical long-term than hCG or clomiphene. Most PCT protocols use Gonadorelin initially then transition to other agents for maintenance.